

A promising finding often begins with a difficult question. In neurology, a research team might notice that patients receiving an intervention recover movement more quickly. In oncology, investigators may observe that one group remains free from disease progression for longer. But how much confidence should they place in these differences?
The reliability of research findings depends on the study design, the outcomes measured, the quality of the collected data and the statistical methods used to analyse the results.
Biostatistical analysis helps researchers examine these questions systematically. It can reduce avoidable errors, clarify uncertainty and guide decisions about what deserves further investigation. It cannot guarantee a breakthrough, but it can help promising research move forward on firmer evidence.
1. Start with the clinical question
Choosing a statistical test should come after defining the question.
Consider a hypothetical neurology study evaluating rehabilitation after stroke. Researchers might investigate walking speed, independence in daily activities or changes in fatigue. Different recovery outcomes provide insights into specific aspects of a patient’s progress, so each requires appropriate measurement methods and assessment criteria.
A useful starting point is to specify:
- Who will participate?
- Which intervention or exposure will be examined?
- What comparison will be made?
- Which outcome matters most?
- When will that outcome be assessed?
In treatment studies, researchers also need to consider events such as treatment discontinuation or switching. The ICH E9(R1) framework helps connect the clinical question with the treatment effect the study intends to estimate.
Agreeing on these details early gives the analysis a clear purpose.
2.Choose outcomes that reflect the research aim
An easily measured outcome is not necessarily the most informative one.
In neurology, a change in a laboratory marker may answer a biological question without establishing whether patients function better. Researchers should explain how their selected measurements relate to the study’s purpose.
Oncology presents similar challenges. Overall survival concerns survival from a defined starting point, while progression-free survival concerns the period during which a patient remains alive without disease worsening. Although these outcomes are closely related, each measures a different aspect of treatment effectiveness and provides distinct insights into patient progress.
Improvement in one outcome should not automatically be presented as improvement in another.
A clear protocol identifies the primary outcome and distinguishes it from secondary or exploratory measurements. This makes the eventual findings easier to interpret and reduces the temptation to emphasise whichever result looks most favourable.
3.Plan sample size before collecting data
“How many participants do we need?” This question cannot be answered accurately without considering the study design, research objectives, expected outcomes and available data.
Sample-size planning depends on the study design, primary outcome, expected variability and the difference researchers want to detect or estimate with useful precision. Anticipated dropout also matters.
For a neurology project involving repeated assessments, the relationship between measurements from the same participant may affect the calculation. For some oncology studies, the number of observed events is particularly important.
A small preliminary study can help assess recruitment and measurement feasibility. However, its estimates may be too uncertain to use uncritically when planning a larger investigation.
Statistical support at this stage helps researchers make their assumptions explicit. It also reveals whether the proposed question is realistic within the available time, budget and access to participants.
4.Build consistency into data collection
Even a carefully chosen model cannot fully repair poorly recorded information.
A neurology study conducted across several centres may involve different assessors, equipment or recording practices. Without clear definitions, apparently comparable measurements may represent different things.
The National Institute of Neurological Disorders and Stroke provides Common Data Elements, including standardised definitions and data-collection resources, to support consistency in neurological research.
Practical preparation includes a data dictionary, consistent units, participant identifiers and agreed rules for recording missing values.
Data checks should identify duplicate records, impossible values and inconsistent dates. Corrections need a documented explanation rather than silent replacement.
For researchers, this preparation can prevent lengthy clarification work when analysis begins and make collaboration across teams more manageable.
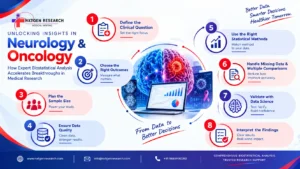
5.Match the analysis to the data
Medical research produces many kinds of information. A symptom score, a hospital admission and the time until disease progression cannot always be analysed in the same way.
In neurology, repeated assessments from one patient are connected. Treating them as unrelated observations can produce misleading estimates of uncertainty. Depending on the question and assumptions, a longitudinal model may be appropriate.
In oncology, time-to-event methods can account for participants whose event time is not fully observed during follow-up. Their interpretation still depends on how follow-up ends and whether the relevant assumptions are reasonable.
Statistical analysis should therefore consider the outcome type, study design, clustering, follow-up and distribution of measurements.
The most effective statistical approach is not necessarily the most complex one; it is the method that best suits the research objectives, data type and study design. A suitable method is one that answers the question and whose assumptions can be examined.
6.Address missing data and multiple comparisons
Missing information deserves investigation. Did a participant miss an appointment, stop treatment or become too unwell to complete an assessment?
These circumstances may have different implications. Excluding records with missing information may reduce the accuracy of statistical estimates and potentially introduce bias into the research findings.
Researchers should plan how missing observations will be handled and examine whether conclusions change under plausible alternative assumptions. Sensitivity analyses help assess how strongly results depend on assumptions that cannot be fully verified.
Multiple comparisons create another challenge. Testing numerous outcomes or subgroups increases the opportunity for chance findings. FDA guidance explains why studies with multiple endpoints need an appropriate strategy for managing this problem.
In neurology and oncology, distinguishing planned analyses from exploratory findings helps readers judge the strength of the evidence.
7.Use data science with appropriate validation
Data science can help researchers explore complex clinical, imaging and molecular information. However, a model that performswell on its development dataset may perform less well with new patients.
For example, a hypothetical neurology model might predict recovery using baseline assessments and imaging features. Before interpreting it as clinically useful, researchers need to examine performance beyond the data used to build it.
The TRIPOD statement highlights the importance of internal validation and evaluation using independent data. Performance assessment includes discrimination—how well predictions distinguish outcomes—andcalibration—how closely predicted risks agree with observed outcomes.
Good prediction also does not establish causation. A variable may help predict an outcome without being a suitable treatment target.
Biostatistical expertise helps keep these distinctions visible.
8.Explain what the findings actually mean
A results section should help readers understand the size, uncertainty and relevance of a finding.
Reporting only whether a p-value crosses a threshold leaves important questions unanswered. How large was the difference? How precise was the estimate? Could it matter clinically?
For neurology studies, a measurable change on a scale should be discussed in relation to what that scale captures. For oncology studies, benefits should be interpreted alongside adverse effects, follow-up and the selected endpoints.
Clear tables and figures support this discussion. Include understandable labels, measurement units, sample sizes and explanations of abbreviations.
Researchers should also describe limitations openly. An association in observational data, for example, may still reflect confounding despite statistical adjustment. Turn careful analysis into useful research
Expert biostatistical analysis supports progress by improving decisions throughout a project: defining the question, planning measurements, checking data, selecting methods and explaining results.
In neurology and oncology, this work can help teams avoid preventable reanalysis and identify which findings justify further investigation. Its value lies in producing evidence that others can examine, question and build upon.
Planning a study or preparing your results for publication? Contact NxtGen Research with your research objectives, study design and timeline to discuss biostatistical analysis and research-reporting support.
FAQ
1.What is biostatistical analysis in neurology research?
Biostatistical analysis applies statistical methods to neurological research data to evaluate outcomes, identify patterns, quantify uncertainty and support reliable interpretation of study findings.
2.Why is sample-size calculation important in medical research?
Sample-size calculation helps researchers plan how many participants are needed to estimate an outcome or detect a meaningful difference with an appropriate level of precision.
3.Which statistical methods are used in neurology studies?
Depending on the research question, methods may include regression analysis, longitudinal models, survival analysis, diagnostic test evaluation and predictive modelling.
4.How does biostatistics support oncology research?
Biostatistics helps oncology researchers analyse treatment outcomes, survival, disease progression, adverse events and other clinical measures while accounting for study design and uncertainty.
5.Why is missing data a concern in clinical research?
Missing data can affect estimates and introduce bias, particularly when the reasons for missingness are related to patient characteristics or outcomes. Researchers should plan and justify their approach to handling it.
6.How can researchers improve the reliability of statistical results?
They can define research questions and outcomes in advance, use suitable study designs, check data quality, evaluate model assumptions, report uncertainty and conduct appropriate sensitivity analyses.
